

A child may struggle to finish a school exercise yet remain interested in a chess position for a long time. That difference deserves curiosity without becoming a medical demonstration. It proves neither the absence of ADHD nor a therapeutic effect of the game.
Chess can be an enjoyable leisure activity and a place to meet others for some people with ADHD. It can also be difficult, tiring or unappealing for others. Here is what the research actually supports and how to offer an activity that respects those differences.
Variable attention does not cancel out difficulties
Attention-deficit/hyperactivity disorder is a developmental disorder that can involve inattention, hyperactivity and impulsivity. According to the NIMH, diagnosis requires persistent symptoms that interfere with functioning in more than one setting, assessed through an appropriate evaluation.
Being absorbed in a game therefore does not rule out ADHD. Conversely, fidgeting, playing quickly or overlooking a piece cannot diagnose it. A coach can describe observations; they do not replace a clinical assessment.
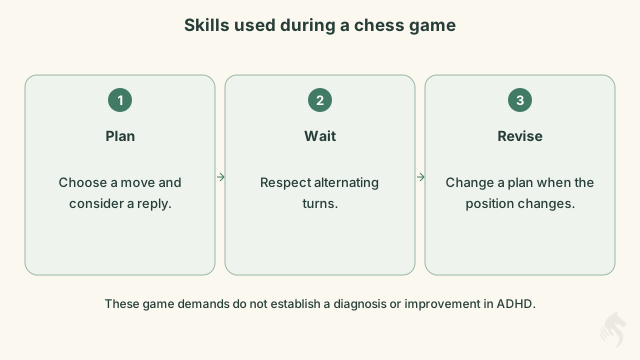
Chess calls on working memory, planning and the ability to interrupt an action to examine a threat. But using a function during a game does not demonstrate lasting improvement or show that progress transfers to homework, employment or everyday life.
Neither magic fuel nor a test of willpower
Describing ADHD as a simple dopamine shortage that the chessboard fills gives an explanation that is too certain and too simple. Interest in a task does not measure a person's neurotransmitters, and the studies cited here do not demonstrate a dopamine correction through chess.
We can observe that a concrete position, an understandable goal or a supportive opponent makes a session more engaging. These are possibilities for adapting the setting, rather than proof of a particular biological mechanism. Our article on dopamine and chess also distinguishes general hypotheses from measured findings.
It would be unfair to conclude: “You concentrate at chess, so you could do the same everywhere if you wanted to.” Demands, surroundings and fatigue change between activities. Enjoying a game does not turn school difficulties into a lack of effort.
What studies of chess and ADHD show
The open pilot study published in 2016
Blasco-Fontecilla and colleagues enrolled 44 children aged 6 to 17 in an 11-week programme. Parent ratings improved after the programme. However, the study was open and had no comparison group; some children were already taking medication. It cannot attribute the changes to chess rather than expectations, support or other changes. The authors themselves call for better-controlled research.
The randomized trial published in 2023
A later trial allocated 104 participants aged 12 to 22 to a cognitive video game, electronic chess exercises or a control group. These activities were added to established medication treatment. The primary outcome, the BRIEF-2 global executive-function score, did not show a significant benefit between groups; neither did the parent-rated SNAP-IV and Conners scales.
Favourable signals on some other measures remain exploratory: mixed findings, many tests, dropouts and a lack of blinding. The journal also warns that the trial was registered retrospectively. These findings validate neither chess as a standalone treatment nor a prescription for ordinary club sessions.
What a chessboard can offer as a setting
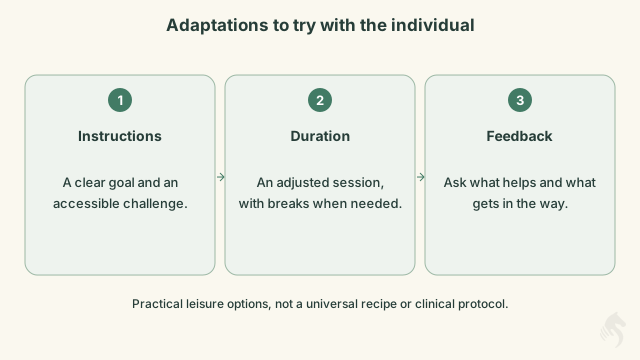
A visible goal. “Find a way to protect this piece” can be more concrete than “improve your concentration.” A short task need not require completing an entire game.
Explicit instructions. Demonstrating one piece's movement, then checking understanding, avoids piling up explanations. The game still has social conventions to explain: waiting for a turn, requesting a break and commenting without humiliation.
An agreed beginning and end. A position to solve, a few moves or a small game can make up a session. A clock is optional; for some people it mainly adds pressure.
A chosen relationship. A patient partner can share an investigation instead of constantly testing ability. Competition suits some players, while others prefer cooperative puzzles.
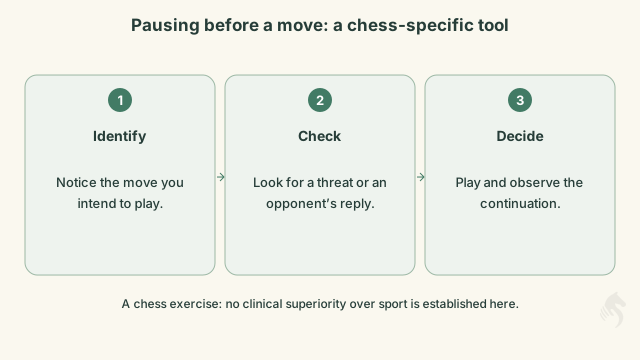
Room to try. A player can be invited to check threats before touching a piece. This reminder supports play; it does not prove that impulsivity is being rehabilitated away from the board.
Starting without turning leisure into a test
First ask whether the person wants to try. These studies establish neither a universal starting age nor an optimal duration for every player with ADHD. A capture game with a few pieces may be enough to explore the board; the full game can follow if interest remains.
Here is an adaptable session example, rather than a therapeutic protocol: choose a small task together, try a position, discuss an interesting move, then decide whether to continue or pause. The goal can simply be an enjoyable shared moment, without a rating target.
Remove one difficulty at a time: too many pieces, too much noise, lengthy instructions or an opponent who is too experienced. Allow players to stand up or return later. Ending a session is not a moral failure, and play need not continue until someone wins.
Physical boards, screens and physical activity
A physical board allows players to handle pieces and meet someone in person. A digital interface may offer convenient access or an available opponent. None of the research presented establishes a general advantage of physical boards over screens for everyone with ADHD.
On a screen, notifications can be disabled, a single activity selected and a stopping point agreed. If fast games keep going at the expense of sleep, responsibilities or enjoyment, reviewing the setting matters more than gaining rating points. These precautions do not demonstrate that online play causes a particular disorder.
Chess need not replace sport either. The activities pose different challenges; a ranking of their supposed effectiveness against ADHD is not established here. Choose according to preferences, access and needs, while keeping room for movement.
Observe the experience instead of promising transfer
To see whether the setting suits someone, ask simple questions: do they want to return? Do they understand the instructions? Can they ask for a break? Are the meetings enjoyable? These observations help adapt leisure without becoming a clinical assessment.
If a family notices changes at school or home, they can discuss them with the professional following the child. Other changes also matter: medication, educational support, sleep and family circumstances. A higher Elo rating does not measure a reduction in ADHD symptoms.
What about adults?
ADHD can persist into adulthood. An adult may enjoy a club, a daily puzzle or a game with friends without any guaranteed benefit to workplace organization or symptoms. Findings from a small trial in young people do not automatically apply to every age.
Adults also have the right to dislike chess. A suitable activity fits into the person's life rather than being imposed by others as a corrective exercise. Our advice on concentration concerns playing the game, rather than treating ADHD.
Where does chess fit alongside care?
The NICE NG87 recommendations set out individualized care: information, environmental adjustments, support and treatments depending on age, difficulties and clinical circumstances. They do not justify presenting chess as a validated substitute for that care.
For persistent difficulties affecting school, work or relationships, seek a professional assessment. Do not change treatment because of a good or bad period of play. A club can welcome people, adapt activities and share the pleasure of learning; it does not need to promise a cure to be worthwhile.
Sources and limitations
- NIMH, Attention-Deficit/Hyperactivity Disorder: What You Need to Know: institutional information about symptoms, assessment and care.
- NICE, Attention deficit hyperactivity disorder: diagnosis and management, NG87: clinical guidance, distinct from a suggested leisure activity.
- Blasco-Fontecilla H. et al. (2016), Efficacy of chess training for the treatment of ADHD: A prospective, open label study, Revista de Psiquiatría y Salud Mental, 9(1), 13-21: open pilot study without a randomized comparison.
- Rodrigo-Yanguas M. et al. (2023), randomized trial of a cognitive video game and electronic chess exercises, JMIR Serious Games, 11, e39874, doi:10.2196/39874: add-on intervention, negative global primary outcome, with methodological limitations detailed in the article.






Comments