

It is 3 a.m. The counter shows 47 games played. Your rating has dropped below the level you wanted to keep. You tell yourself: “Just one more, the game that puts things right.” Ending on a loss suddenly feels impossible.
This scene is a fictional example, not a statistic about players on Chess.com or Lichess. It raises a practical question: what can you do when a chosen activity starts eating into sleep, relationships or work?
Chess can be a demanding passion, a social life and a lasting pleasure. Intense involvement alone does not establish an addiction. Equally, its reputation as an intellectual game does not make a persistent loss of control harmless. A useful discussion distinguishes engagement, problematic use and clinical diagnosis, without turning every wish for a rematch into an illness.
Addiction is not limited to substances
The World Health Organization describes gaming disorder in ICD-11 as a disorder involving digital or video gaming. Its central features include difficulty controlling gaming, increasing priority given to it, and continuing despite negative consequences. The impact on everyday functioning must be significant; the pattern is normally evident for at least twelve months.
That does not mean waiting a year before asking for help. Nor does every long session indicate this disorder. Duration, circumstances and consequences require clinical assessment. The category is not, by itself, a study of how common “chess addiction” might be.
There is another distinction: the American Psychiatric Association presents Internet Gaming Disorder in DSM-5-TR as a condition requiring further research. Its status and criteria therefore differ from those in ICD-11. A blog article cannot make that diagnosis or automatically apply these categories to a chess player.
A simpler starting point is: can you still choose when to play and when to stop, and what is this activity costing you? That question matters even when someone's difficulties do not meet a diagnostic threshold.
Reward and habits: explaining them without inventing a brain scan
Dopamine is not a victory counter
The shortcut “win → dopamine spike → addiction” sounds convincing, but goes too far. Research by Schultz, Dayan and Montague (1997) links dopamine signals to learning reward predictions, including experiments with primates. It does not measure a dose of dopamine after every checkmate on an app.
Enjoying a beautiful move, feeling surprised and wanting to regain a rating can all contribute to motivation in chess. They do not tell us the state of a reader's striatum, the intensity of a “spike”, or whether it is equivalent to a substance's effects. A general account of learning is not a neurological measurement of blitz.
The I-PACE model proposed by Brand and colleagues (2019) examines interactions between personal characteristics, emotions, expectations, responses to cues and behavioral control. This theoretical framework helps formulate hypotheses; it does not establish that every platform notification triggers chess addiction.
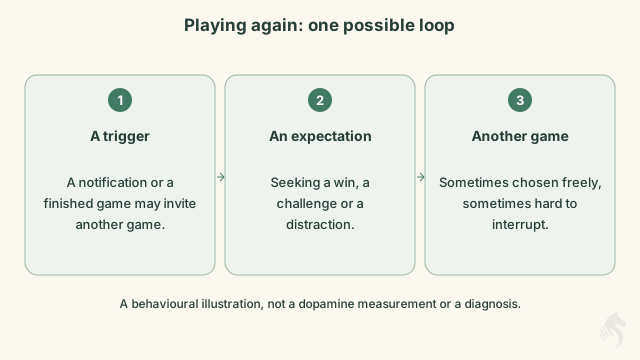
Uncertainty can make another game appealing
You do not know the result of your next game. After a frustrating loss, the prospect of “getting even” may become more appealing than studying the position. Immediate access to another opponent leaves little time to consider whether you actually want to continue.
That is one possible interpretation of a player's experience, not proof that chess reproduces a casino protocol or an experimental variable-ratio reinforcement schedule. A game involves decisions, skills and an opponent. Directly transferring findings about gambling or substances to chess would require appropriate studies.
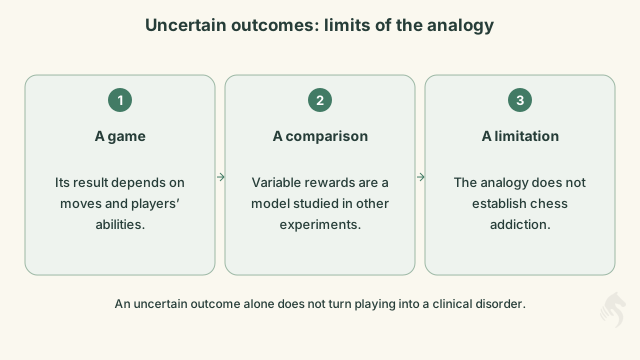
When an urge becomes difficult to interrupt
Wanting to play after a busy day is not inherently worrying. A different situation is starting another game despite exhaustion, regularly regretting a session or repeatedly failing to keep the limits you had set.
We can describe that difficulty without claiming that the prefrontal cortex has been “short-circuited”. Your experience, habits and observable consequences already provide useful information for understanding the problem and discussing it.
Three situations to notice in online chess
These examples are neither specific symptoms nor a validated list of causal factors. They invite you to examine what playing means to you.
The number that defines you: when ratings take up too much space
A rating places sporting results in context. It measures neither your personal worth nor your intelligence. Yet moving from “my rating is 1600” to “I am a 1600” can make every change feel painfully important.
If you start a game to erase a rating drop rather than because you want to play, note that motivation. Then compare it with a session spent studying a position or analyzing a game. Psychology of the chess player explores this relationship with results. The aim is not to ban ratings, but to examine their place in your life.
Community as a connection
Online clubs, friends and tournaments can provide meaningful relationships. They can also make taking a break difficult if you fear missing an event or disappointing your group.
Telling partners when you plan to stop or suggesting an activity away from the platform can help you notice this tension. Belonging to a community is not a sign of illness; a possible problem is no longer being able to protect your other commitments.
Playing to put everything else at a distance
A game can offer a welcome break on a difficult day. If it becomes your only way to cope with worry, loneliness or conflict, it is worth examining that context too.
We cannot infer from an imaging study that the “default mode network” switches off a player's worries. The relief you feel and the difficulties that return after a session deserve to be described in their own right. Associated anxiety or low mood also does not establish which difficulty came first.
Tilt: describing the spiral without invented cortisol measurements
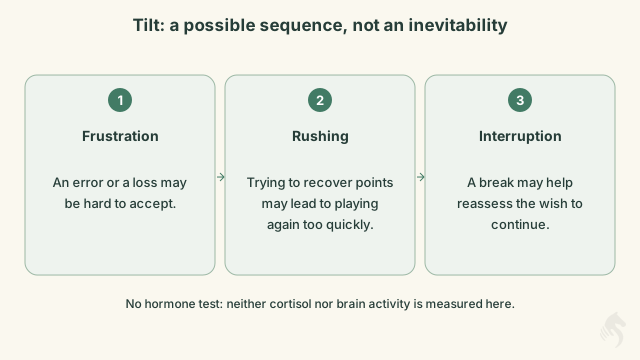
You lose a game, immediately start another and become more irritated. Players use tilt to describe the point where frustration weighs on decisions and on the urge to keep playing.
There is no need to say that “the amygdala takes the wheel”. We have no measurement here that could compare cortisol during blitz with a first parachute jump. That comparison should not serve as medical evidence.
The practical sign is a change in behavior: rushing without thinking, insulting an opponent, repeatedly postponing bedtime or continuing only to recover rating points. A break allows time to step back; it does not guarantee a win when you return, and it cannot replace support when difficulties persist.
Taking stock without diagnosing yourself
These are questions for reflection, not a validated screening test:
- Do you regularly play longer than intended?
- Does chess affect sleep, school, work or relationships?
- Do attempts to cut back repeatedly fail?
- Do you continue despite consequences you clearly recognize?
- Has chess become your only way to ease tension?
There is no “three yes answers = addiction” rule. A significant difficulty can warrant a consultation without reaching an arbitrary score. Conversely, recognizing yourself in one question is not enough to establish a disorder.
To prepare for a conversation with a professional, record specific situations: starting and finishing times, your intended limit, sleep, missed commitments, and how you felt before and after. A doctor or mental health professional can assess the whole situation, including any associated difficulties. The aim is appropriate support, not a label.
Available figures do not give a rate of chess addiction
A rise in registrations after a television series, or a platform's account count, does not measure an illness. An account is not necessarily an active person; an active person does not necessarily have problematic use.
Video-gaming surveys use different populations and instruments. Their results cannot be presented as the percentage of chess players with addiction. The sources cited here do not provide such a chess-specific estimate.
That limitation does not make your experience imaginary. When deciding whether to seek support, the consequences you observe matter more than a spectacular number about the game's popularity.
Three adjustments to try, without presenting them as treatment
Step 1: choose a pace compatible with your life
If quick rematches prolong sessions, try an activity that limits them: a scheduled game, analysis, a puzzle on paper or a club meeting. A slower time control may change the experience, but it can also lengthen a session.
First choose a time slot that respects your commitments and sleep. There is no prescribed “10+0 minimum” or daily game count here for treating addiction. If you cannot keep those boundaries, that deserves discussion rather than being treated as a moral failure.
Step 2: put ratings in perspective
An unrated session or a learning goal may help you notice what you enjoy beyond the score. Observe what changes without promising yourself that one week will be enough.
Ryan and Deci's self-determination theory distinguishes forms of motivation and examines autonomy, competence and relationships. It offers a framework for reflecting on playing; it does not demonstrate that hiding a graph treats chess addiction.
Step 3: decide when to finish before you begin
You can set an end time, plan a break or agree on a limit with someone you trust. “Three games maximum” is one example of a personal rule, not a clinical threshold or validated withdrawal method. If the rule itself becomes a source of tension, review it with support.
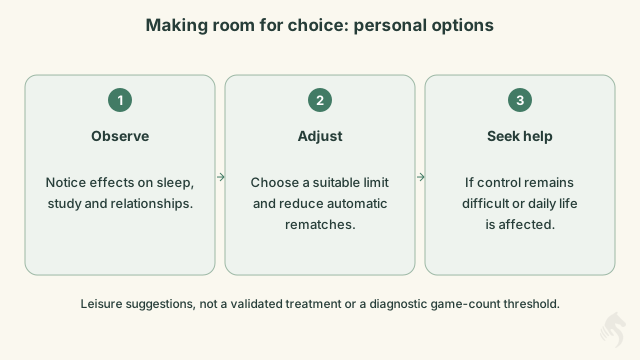
Reducing notifications and keeping your phone away from bed may make boundaries easier to keep. For persistent loss of control, distress or significant effects on everyday life, contact a health professional. In France, Addictions France also describes support options. A young person can speak to a trusted adult or a school health professional.
Beyond 64 squares: understanding what playing provides
For some people, chess offers connection; for others, competition, curiosity or a break. There is no single psychological cause behind all difficult patterns of use. Automatically looking for “escape” or a character flaw can obscure the real situation.
A useful question is: what does this activity provide, and what other ways of meeting that need remain available? You can love chess deeply and still need to change how it occupies your day.
Being free to play and to stop
The goal is not to earn the title of “real player” by managing every habit alone. It is to regain a pattern of play compatible with the rest of your life, with support if needed.
After reading: choose one observable change, then record what actually happens. Sleep and keeping your intended finishing time are more useful markers than a promise to “reset dopamine”. If the consequences are already significant, seek help without waiting for a personal experiment to end.
Sources and references
- WHO, Gaming disorder, ICD-11 questions and answers: definition, impact and usual duration. Institutional page.
- American Psychiatric Association, Internet Gaming: IGD's status in DSM-5-TR and the distinction between engagement and disorder. Institutional page.
- Brand, M. et al. (2019), The Interaction of Person-Affect-Cognition-Execution (I-PACE) model for addictive behaviors: Update…, Neuroscience & Biobehavioral Reviews, 104, 1-10. A theoretical framework, not a clinical study of chess. Record and abstract.
- Schultz, W., Dayan, P. and Montague, P. R. (1997), A Neural Substrate of Prediction and Reward, Science, 275, 1593-1599. Authors' text.
- Ryan, R. M. and Deci, E. L. (2000), Self-Determination Theory and the Facilitation of Intrinsic Motivation, Social Development, and Well-Being, American Psychologist, 55, 68-78. Authors' text.






Comments